Inflamed gut and a closing surface
KPV in the Cowboy Up Peptide ledger
A mouse regaining weight and a rabbit cornea closing give this small peptide several very different meanings of recovery.
Body weight after colitis
A mouse regaining weight after colitis is a more concrete subject than “inflammation support.” In Kannengiesser and colleagues’ 2008 mouse experiments, KPV was associated with earlier recovery and stronger regain of body weight in the DSS colitis model, alongside less inflammatory infiltrate and lower myeloperoxidase activity. The work included chemically induced colitis and an adoptive-transfer model.
Those observations make a stronger case together, to my mind. Weight regain describes the animal; tissue infiltration and enzyme activity describe aspects of its inflamed colon. Each measurement leaves something out, but together they provide a more substantial account of recovery than a single pathway name.
The study also included mice deficient in MC1R, a melanocortin receptor. KPV’s anti-inflammatory activity persisted. That finding complicates the assumption that a fragment of a hormone must work through the parent hormone’s familiar receptor route.
Lysine, proline, valine
KPV consists of those three amino acids, corresponding to residues 11–13 at the end of alpha-melanocyte-stimulating hormone, or alpha-MSH. Its other name, alpha-MSH(11-13), records that position. The molecular formula is C16H30N4O4.
The 2008 review of alpha-MSH and related tripeptides describes KPV’s anti-inflammatory activity together with its lack of the full hormone’s pigment-producing action. That distinction matters when the compound gets swept into talk of tanning peptides. Here the useful research questions concern inflamed tissue and wound repair.
Cellular inflammation experiments
Dalmasso and colleagues studied human intestinal epithelial cell lines and Jurkat T cells in vitro, as well as chemically induced colitis in mice. PepT1, a transporter for small peptides, carried KPV into intestinal cells. In those cellular experiments, nanomolar KPV reduced NF-kB and MAP-kinase activation and pro-inflammatory cytokine secretion. Oral KPV also reduced colitis severity in the DSS and TNBS mouse models.
There is a useful complication in the earlier 2003 fragment-comparison experiment. KPV reduced leukocyte accumulation in a mouse peritonitis model, yet it did not suppress macrophage cytokine release as the core MSH peptides did. The authors favored a distinct, likely IL-1beta-directed explanation. I resist turning all of that into a universal “off switch.” The cell type and the experimental challenge deserve their place in the account.
Rabbit corneal wounds
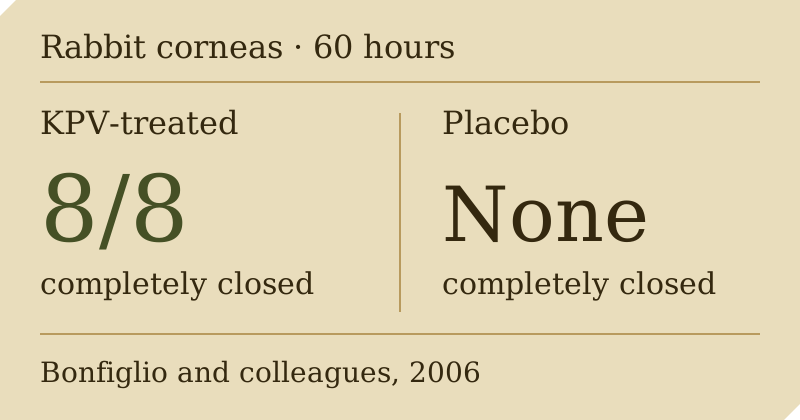
The 2006 rabbit study by Bonfiglio and colleagues moved the question to the eye’s surface. Topical KPV accelerated corneal epithelial wound healing through a nitric-oxide-dependent mechanism. By 60 hours, 8/8 KPV-treated corneas were completely re-epithelialized, versus none in the placebo group. Re-epithelialization is the surface layer closing over the wound.
I appreciate the plainness of that endpoint: was the surface closed at the stated time? The answer is specific to rabbit corneas and that experiment. It leaves human eye treatment, other wounds and systemic safety to further research.
Materials around the peptide
Free KPV is vulnerable to peptide-degrading enzymes, and no validated human pharmacokinetic profile is established. That helps explain the attention to delivery materials. In Xiao and colleagues’ 2017 mouse colitis study, hyaluronic-acid-functionalized nanoparticles carrying KPV were embedded in a chitosan/alginate hydrogel. The targeted formulation reduced mucosal damage and TNF-alpha and accelerated healing more effectively than non-targeted delivery.
A 2024 mouse study co-assembled KPV with the immunosuppressant FK506 in a PepT1-targeted nanodrug. It improved acute and chronic colitis outcomes beyond either agent alone, including restoration of tight-junction proteins. Those proteins help seal neighboring cells. The formulation deserves a share of the credit: these experiments tested a constructed delivery system, and the combination also contained another active agent.

Human evidence and access
KPV’s published efficacy record here consists of cells and animals. There are no published human clinical trials or validated human dosing and safety data. The intestinal study and the oral-delivery experiment make the potential worth investigating; they leave the human benefit-risk question open.
KPV has no approved drug or dietary-supplement status in any major jurisdiction. Research-labelled material remains sold for laboratory work; prescription access requires a licensed U.S. provider’s assessment and decision, and not everyone qualifies. Compounded medicines are not FDA-approved. KPV has no established name-specific WADA classification in this record; its non-approved status still warrants caution in regulated sport.
A corneal experiment following function after closure would interest me. The result is interesting enough to deserve that question. For the other compound’s very different record, see BPC-157.